

TMS, short for transcranial magnetic stimulation, is a non-invasive treatment that uses magnetic pulses to stimulate a specific area of the brain involved in mood regulation. It does not involve medication, anesthesia, or surgery, and most patients drive themselves to and from every appointment. It was first cleared by the FDA for depression in 2008 and has since been cleared for additional conditions. This guide covers what it actually is, what it treats, what a course looks like, and how well it works, in plain terms.
What We Know
|
What is TMS Therapy?
During a TMS session at Village TMS, a coil positioned against your scalp generates a magnetic field that passes painlessly through skin and skull to induce a small electrical current in the brain’s outer layer. That current activates neurons in the targeted region, the same way exercise activates a muscle, with the goal of restoring healthier activity in brain circuits involved in mood. Unlike antidepressant medication, nothing enters your bloodstream, which is why TMS avoids the systemic side effects associated with pills, such as weight gain, sexual dysfunction, or sedation.
A brief history and FDA clearance timeline
- 2008: TMS receives its first FDA clearance, for adults with major depressive disorder who have not responded to at least one antidepressant medication
- 2013: A second-generation coil is cleared for adults with depression who have failed any number of prior treatments
- 2018: Deep TMS is cleared as an adjunctive treatment for obsessive-compulsive disorder, based on a controlled trial showing meaningfully higher response rates than sham treatment
- 2019: TMS is cleared for anxious depression, meaning major depressive disorder with significant co-occurring anxiety symptoms
Each clearance required its own controlled clinical trial data, which is part of why TMS carries a stronger evidence base than many newer brain stimulation approaches still confined to research settings.

What conditions TMS treats
Treatment-resistant depression
This remains the core, most established use of TMS: adults with major depressive disorder who have not achieved adequate improvement from at least one prior antidepressant trial.
Obsessive-compulsive disorder
TMS for OCD uses a different coil and protocol than the depression protocol, often including brief, controlled exposure to a patient’s triggers immediately before stimulation. It is FDA-cleared as an adjunctive treatment, meaning it is intended to be used alongside other approaches such as exposure and response prevention therapy rather than as a stand-alone replacement.
Anxious depression
For patients whose depression comes with significant anxiety, TMS has separate FDA clearance and its own body of supporting research, generally showing a real but more moderate benefit compared to depression alone.
Who is a candidate for TMS
A good candidate has typically tried at least one antidepressant without adequate relief, has no personal history of seizures, has no non-removable magnetic or metal implants near the head, and does not have unstable bipolar disorder. A full psychiatric evaluation, not a checklist alone, is the only reliable way to confirm candidacy.
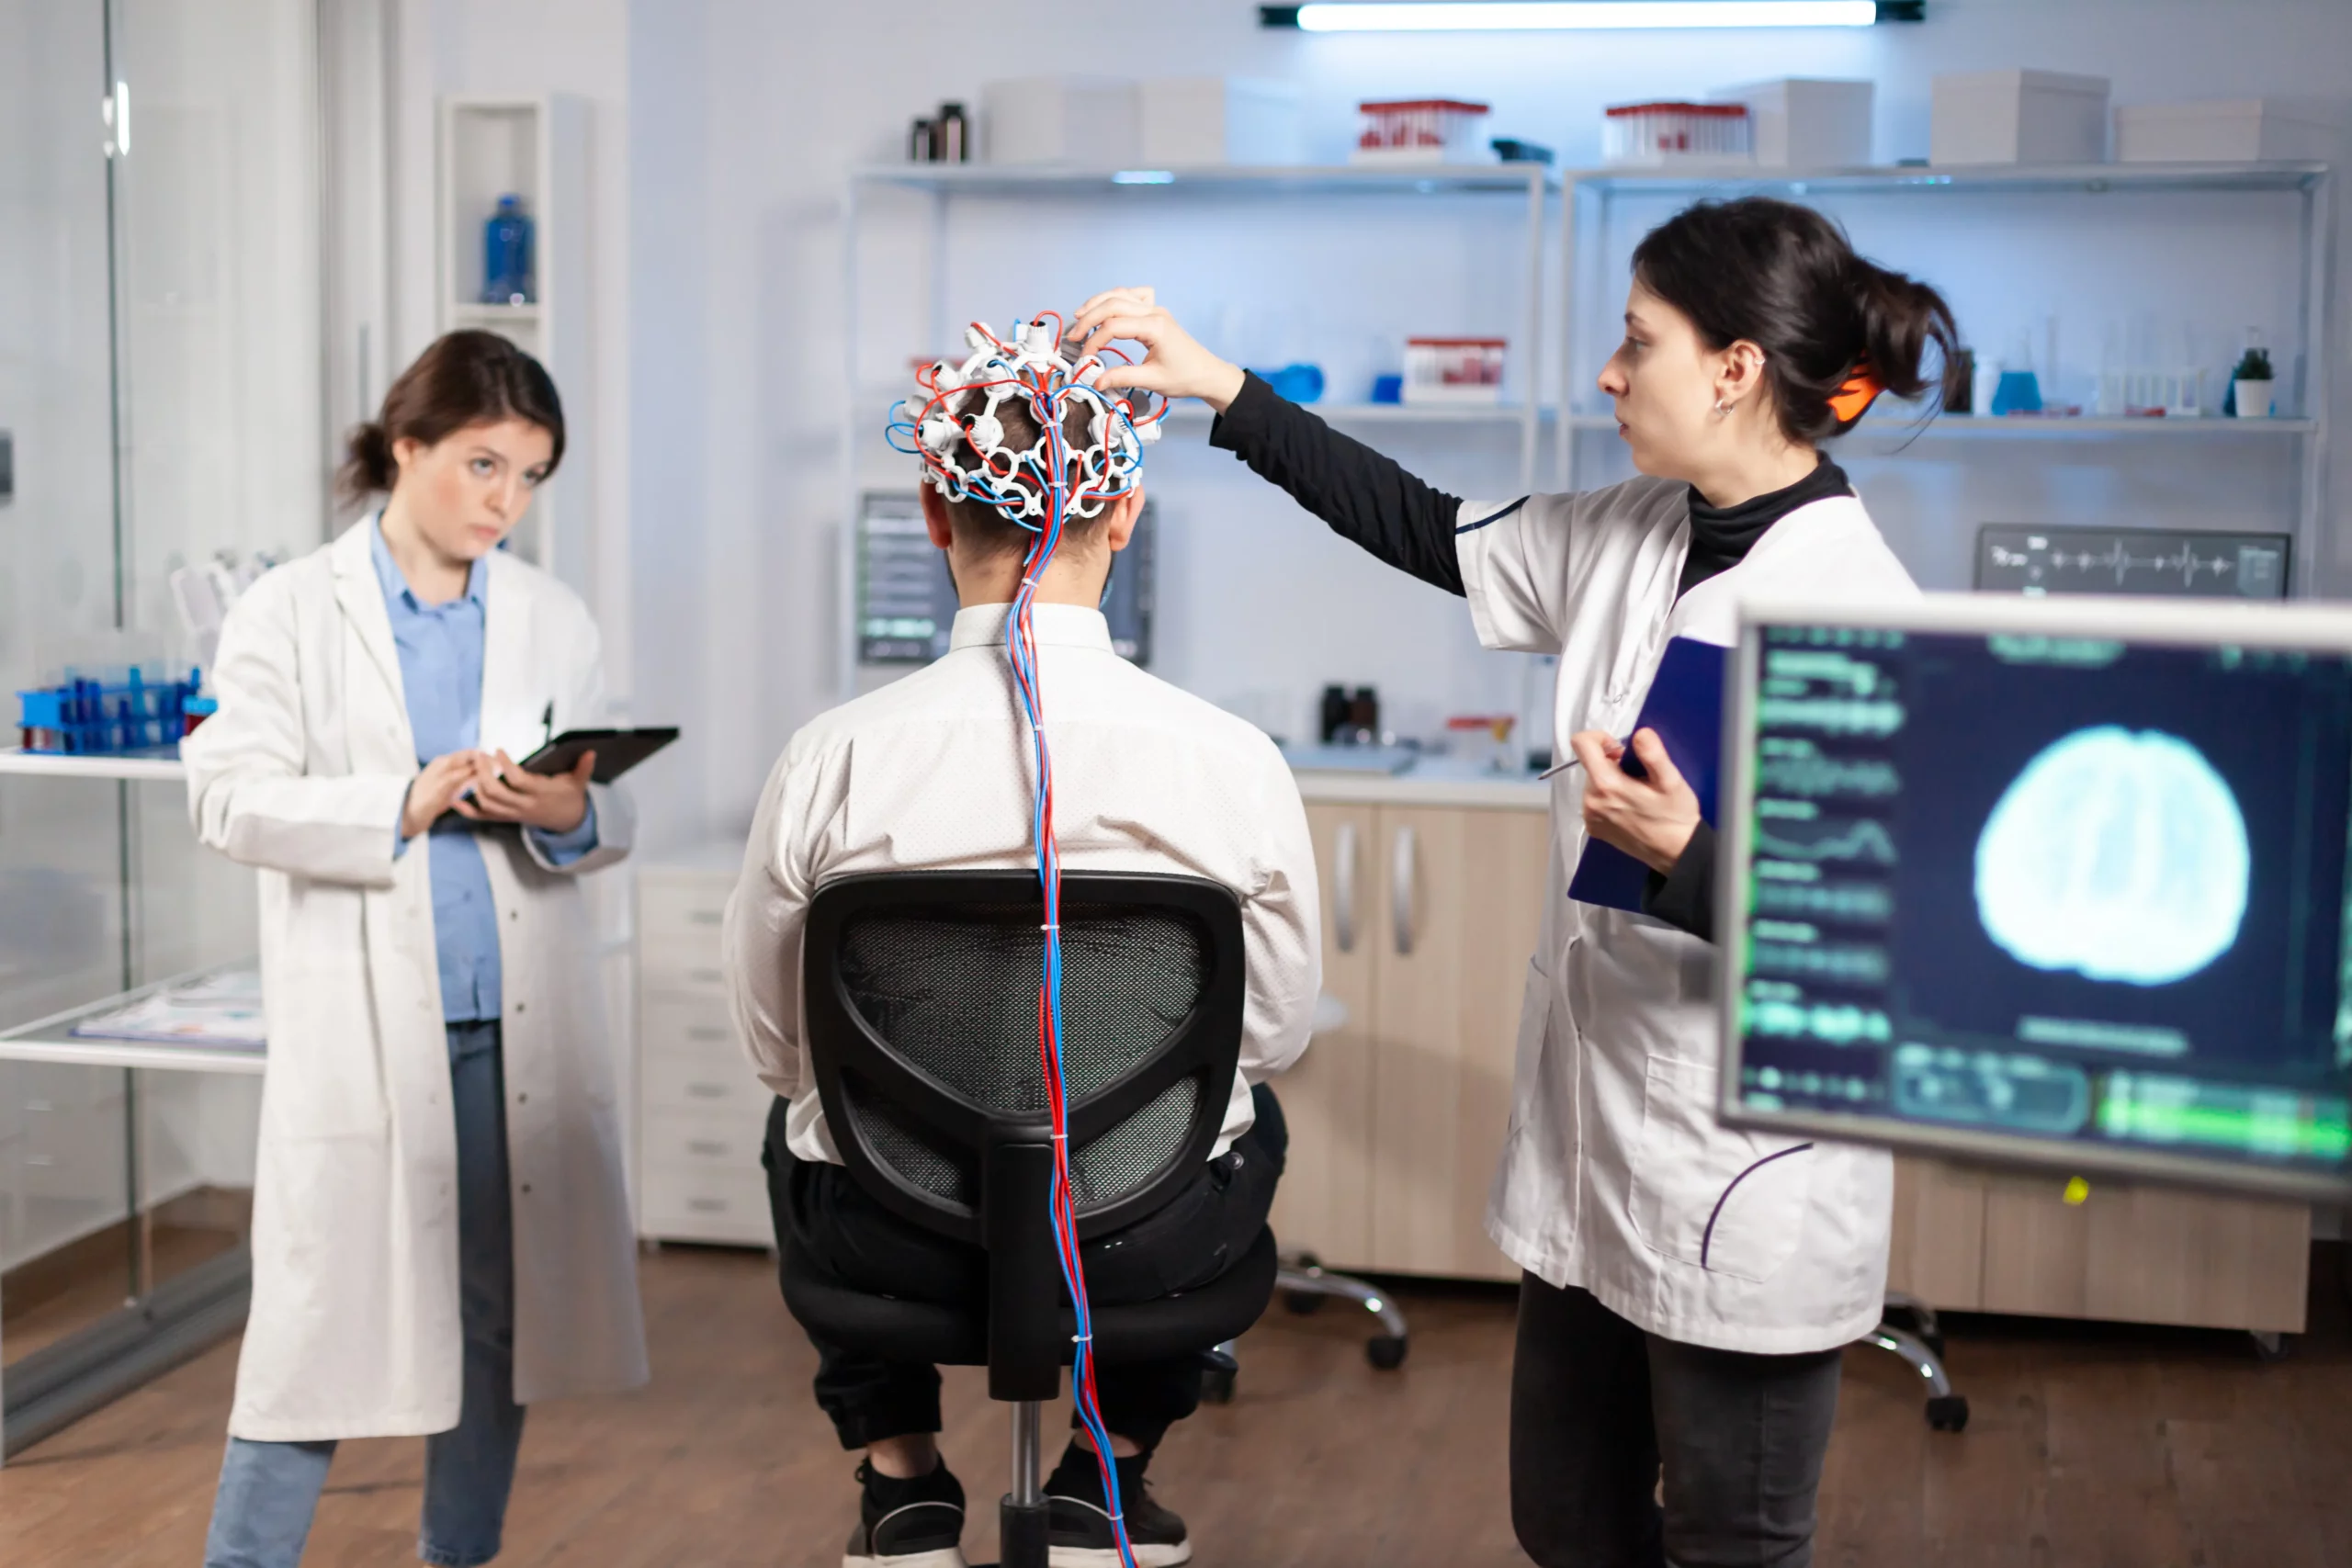
What a session and full course look like
Every course begins with motor threshold calibration, an individualized measurement that sets your personal treatment dose. After that, sessions run 20 to 40 minutes, five days a week, for four to six weeks, with most patients returning to normal activities immediately afterward. A separate article on this site walks through the session-by-session mechanics and week-by-week experience in more depth.
How effective is TMS
For treatment-resistant depression, clinical trial response rates generally run 50 to 60 percent, with remission around 30 to 40 percent. An NIMH-sponsored, sham-controlled trial found significantly higher response and remission rates with active TMS than with sham stimulation, which is the kind of controlled comparison that distinguishes a real treatment effect from a placebo response.
Side effects, briefly
Most patients experience mild, localized side effects such as scalp discomfort or headache during the first week or two, which typically ease as treatment continues. Serious side effects like seizure are rare, estimated at roughly 1 in 1,000 patients under standard clinical protocols. A dedicated article on this site covers the full side effect picture and timeline in detail.
Cost and insurance
TMS is covered by most major insurers for treatment-resistant depression, typically after documentation that at least one prior antidepressant trial did not produce adequate improvement. Coverage details, including prior authorization requirements, vary by plan.
Call 646-817-2835 or contact us to book a free consultation.






